Skin cancers are
cancers that arise from the
skin. They are due to the development of abnormal
cells that have the ability to invade or
spread to other parts of the body.
[10] There are three main types of skin cancers:
basal-cell skin cancer (BCC),
squamous-cell skin cancer (SCC) and
melanoma.
[1] The first two, along with a number of less common skin cancers, are known as nonmelanoma skin cancer (NMSC).
[5][11] Basal-cell cancer grows slowly and can damage the tissue around it but is unlikely to spread to distant areas or result in death.
[5] It often appears as a painless raised area of skin that may be shiny with
small blood vessels running over it or may present as a raised area with an
ulcer.
[1] Squamous-cell skin cancer is more likely to spread.
[5] It usually presents as a hard lump with a scaly top but may also form an ulcer.
[2] Melanomas are the most aggressive. Signs include a
mole that has changed in size, shape, color, has irregular edges, has more than one color, is itchy or bleeds.
[3]
More than 90% of cases are caused by exposure to
ultraviolet radiation from the
Sun.
[4] This exposure increases the risk of all three main types of skin cancer.
[4] Exposure has increased, partly due to a thinner
ozone layer.
[5][12] Tanning beds are another common source of ultraviolet radiation.
[4] For melanomas and basal-cell cancers, exposure during childhood is particularly harmful.
[6] For squamous-cell skin cancers, total exposure, irrespective of when it occurs, is more important.
[4] Between 20% and 30% of melanomas develop from moles.
[6] People with lighter skin are at higher risk
[1][13] as are those with poor immune function such as from medications or
HIV/AIDS.
[5][14] Diagnosis is by
biopsy.
[3]
Decreasing exposure to ultraviolet radiation and the use of
sunscreen appear to be effective methods of preventing melanoma and squamous-cell skin cancer.
[6][7] It is not clear if sunscreen affects the risk of basal-cell cancer.
[7] Nonmelanoma skin cancer is usually curable.
[5] Treatment is generally by surgical removal but may, less commonly, involve
radiation therapy or topical medications such as
fluorouracil.
[1] Treatment of melanoma may involve some combination of surgery,
chemotherapy,
radiation therapy and
targeted therapy.
[3] In those people whose disease has spread to other areas of the body,
palliative care may be used to improve quality of life.
[3] Melanoma has one of the higher survival rates among cancers, with over 86% of people in the UK and more than 90% in the United States
surviving more than 5 years.
[15][16]
Skin cancer is the most common form of cancer, globally accounting for at least 40% of cancer cases.
[5][17] The most common type is nonmelanoma skin cancer, which occurs in at least 2–3 million people per year.
[6][18] This is a rough estimate, however, as good statistics are not kept.
[1] Of nonmelanoma skin cancers, about 80% are basal-cell cancers and 20% squamous-cell skin cancers.
[11] Basal-cell and squamous-cell skin cancers rarely result in death.
[6] In the United States, they were the cause of less than 0.1% of all cancer deaths.
[1] Globally in 2012, melanoma occurred in 232,000 people and resulted in 55,000 deaths.
[6] White people in
Australia,
New Zealand and
South Africa have the highest rates of melanoma in the world.
[6][19] The three main types of skin cancer have become more common in the last 20 to 40 years, especially in those areas with mostly White people.
[5][6]
Classification[edit]
| Cancer | Description | Illustration |
|---|
| Basal-cell carcinoma | Note the pearly translucency to fleshy color, tiny blood vessels on the surface, and sometimes ulceration which can be characteristics. The key term is translucency. |
|
| Squamous-cell skin carcinoma | Commonly presents as a red, crusted, or scaly patch or bump. Often a very rapidly growing tumor. |
|
| Malignant melanoma | These are commonly asymmetrical in shape and/or pigment distribution, with an irregular border, color variation, and often greater than 6 mm diameter.[20] |
|
Basal-cell carcinomas are most commonly present on sun-exposed areas of the skin, especially the face. They rarely metastasize and rarely cause death. They are easily treated with surgery or radiation. Squamous-cell skin cancers are also common, but much less common than basal-cell cancers. They metastasize more frequently than BCCs. Even then, the metastasis rate is quite low, with the exception of SCC of the lip, ear, and in people who are immunosuppressed. Melanoma are the least frequent of the three common skin cancers. They frequently metastasize, and potentially cause death once they spread.
Less common skin cancers include:
dermatofibrosarcoma protuberans,
Merkel cell carcinoma,
Kaposi's sarcoma,
keratoacanthoma, spindle cell tumors,
sebaceous carcinomas,
microcystic adnexal carcinoma,
Paget's disease of the breast, atypical fibroxanthoma,
leiomyosarcoma, and
angiosarcoma.
BCC and SCC often carry a UV-signature mutation indicating that these cancers are caused by
UVB radiation via direct DNA damage. However malignant melanoma is predominantly caused by UVA radiation via indirect DNA damage. The indirect DNA damage is caused by free radicals and reactive oxygen species. Research indicates that the absorption of three sunscreen ingredients into the skin, combined with a 60-minute exposure to UV, leads to an increase of
free radicals in the skin, if applied in too little quantity and too infrequently.
[21] However, the researchers add that newer creams often do not contain these specific compounds, and that the combination of other ingredients tends to retain the compounds on the surface of the skin. They also add that frequent re-application reduces the risk of radical formation.
Signs and symptoms[edit]
There are a variety of different skin cancer symptoms. These include changes in the
skin that do not heal,
ulcering in the skin, discolored skin, and changes in existing
moles, such as jagged edges to the mole and enlargement of the mole.
Basal-cell skin cancer[edit]
Basal-cell skin cancer (BCC) usually presents as a raised, smooth, pearly bump on the sun-exposed skin of the
head,
neck,
torso or
shoulders. Sometimes small
blood vessels (called
telangiectasia) can be seen within the tumor. Crusting and bleeding in the center of the tumor frequently develops. It is often mistaken for a sore that does not heal. This form of skin cancer is the least deadly, and with proper treatment can be completely eliminated, often without significant scarring.
Squamous-cell skin cancer[edit]
Squamous-cell skin cancer (SCC) is commonly a red, scaling, thickened patch on sun-exposed skin. Some are firm hard nodules and dome shaped like
keratoacanthomas. Ulceration and bleeding may occur. When SCC is not treated, it may develop into a large mass. Squamous-cell is the second most common skin cancer. It is dangerous, but not nearly as dangerous as a melanoma.
Melanoma[edit]
Most melanoma consist of various colours from shades of brown to black. A small number of melanoma are pink, red or fleshy in colour; these are called amelanotic melanoma and tend to be more aggressive. Warning signs of malignant melanoma include change in the size, shape, color or elevation of a mole. Other signs are the appearance of a new mole during adulthood or pain, itching, ulceration, redness around the site, or bleeding at the site. An often-used mnemonic is "ABCDE", where A is for "asymmetrical", B for "borders" (irregular: "Coast of Maine sign"), C for "color" (variegated), D for "diameter" (larger than 6 mm – the size of a pencil eraser) and E for "evolving."
[22][23]
Merkel cell carcinomas are most often rapidly growing, non-tender red, purple or skin colored bumps that are not painful or itchy. They may be mistaken for a cyst or another type of cancer.
[24]
Ultraviolet radiation from sun exposure is the primary environmental cause of skin cancer.
[25][26][27] This can occur in professions such as farming. Other risk factors that play a role include:
- Smoking tobacco[26]
- HPV infections increase the risk of squamous-cell skin cancer.[26]
- Some genetic syndromes[26] including congenital melanocytic nevi syndrome which is characterized by the presence of nevi (birthmarks or moles) of varying size which are either present at birth, or appear within 6 months of birth. Nevi larger than 20 mm (3/4") in size are at higher risk for becoming cancerous.
- Chronic non-healing wounds.[26] These are called Marjolin's ulcers based on their appearance, and can develop into squamous-cell skin cancer.
- Ionizing radiation such as X-rays, environmental carcinogens, artificial UV radiation (e.g. tanning beds), aging, and light skin color.[26] It is believed that tanning beds are the cause of hundreds of thousands of basal and squamous-cell skin cancer.[28] The World Health Organization now places people who use artificial tanning beds in its highest risk category for skin cancer.[29] Alcohol consumption, specifically excessive drinking increase the risk of sunburns.[30]
- The use of many immunosuppressive medications increases the risk of skin cancer. Cyclosporin A, a calcineurin inhibitor for example increases the risk approximately 200 times, and azathioprine about 60 times.[31]
Pathophysiology[edit]
A malignant epithelial tumor that primarily originates in the epidermis, in squamous mucosa or in areas of squamous metaplasia is referred to as a squamous-cell carcinoma.
[32]
Macroscopically, the tumor is often elevated,
fungating, or may be ulcerated with irregular borders. Microscopically, tumor cells destroy the
basement membrane and form sheets or compact masses which invade the subjacent connective tissue (dermis). In well differentiated carcinomas, tumor cells are
pleomorphic/atypical, but resembling normal keratinocytes from prickle layer (large, polygonal, with abundant
eosinophilic (pink) cytoplasm and central nucleus).
[32]
Their disposal tends to be similar to that of normal epidermis: immature/basal cells at the periphery, becoming more mature to the centre of the tumor masses. Tumor cells transform into
keratinized squamous cells and form round nodules with concentric, laminated layers, called "cell nests" or "epithelial/keratinous pearls". The surrounding stroma is reduced and contains inflammatory infiltrate (lymphocytes). Poorly differentiated squamous carcinomas contain more pleomorphic cells and no
keratinization.
[32]
A molecular factor involved in the disease process is mutation in gene
PTCH1 that plays an important role in the
Sonic hedgehog signaling pathway.
[33]
Diagnosis[edit]
Non-invasive skin cancer detection methods include photography, dermoscopy, sonography,
confocal microscopy, Raman spectroscopy, fluorescence spectroscopy, terahertz spectroscopy, optical coherence tomography, the multispectral imaging technique, thermography, electrical bio-impedance, tape stripping and computer-aided analysis.
[34]
Computer-assisted diagnosis devices have been developed that analyze images from a
dermatoscope or spectroscopy and can be used by a diagnostician to aid in the detection of skin cancer. CAD systems have been found to be highly sensitive in the detection of melanoma, but have a high false-positive rate. There is not yet enough evidence to recommend CAD as compared to traditional diagnostic methods.
[35]
Prevention[edit]
Sunscreen is effective and thus recommended to prevent melanoma
[37] and squamous-cell carcinoma.
[38] There is little evidence that it is effective in preventing basal-cell carcinoma.
[39] Other advice to reduce rates of skin cancer includes avoiding sunburning, wearing protective clothing, sunglasses and hats, and attempting to avoid sun exposure or periods of peak exposure.
[40] The
U.S. Preventive Services Task Force recommends that people between 9 and 25 years of age be advised to avoid ultraviolet light.
[41]
The risk of developing skin cancer can be reduced through a number of measures including decreasing
indoor tanning and mid day sun exposure, increasing the use of
sunscreen,
[42] and avoiding the use of
tobacco products.
There is insufficient evidence either for or against screening for skin cancers.
[43] Vitamin supplements and
antioxidant supplements have not been found to have an effect in prevention.
[44] Evidence for reducing melanoma risk from dietary measures is tentative, with some supportive epidemiological evidence, but no clinical trials.
[45]
Eating certain foods may decrease the risk of sunburns but this is much less than the protection provided by sunscreen.
[47]
A meta-analysis of skin cancer prevention in high risk individuals found evidence that topical application of T4N5 liposome lotion reduced the rate of appearance of basal cell carcinomas in people with
xeroderma pigmentosum, and that
acitretin taken by mouth may have a skin protective benefit in people following
kidney transplant.
[48]
Treatment[edit]
Treatment is dependent on the specific type of cancer, location of the cancer, age of the person, and whether the cancer is primary or a recurrence. For a small
basal-cell cancer in a young person, the treatment with the best cure rate (
Mohs surgery or
CCPDMA) might be indicated. In the case of an elderly frail man with multiple complicating medical problems, a difficult to excise basal-cell cancer of the nose might warrant radiation therapy (slightly lower cure rate) or no treatment at all. Topical chemotherapy might be indicated for large superficial basal-cell carcinoma for good cosmetic outcome, whereas it might be inadequate for invasive nodular
basal-cell carcinoma or invasive
squamous-cell carcinoma.
[citation needed] In general, melanoma is poorly responsive to radiation or chemotherapy.
Mohs' micrographic surgery (
Mohs surgery) is a technique used to remove the cancer with the least amount of surrounding tissue and the edges are checked immediately to see if tumor is found. This provides the opportunity to remove the least amount of tissue and provide the best cosmetically favorable results. This is especially important for areas where excess skin is limited, such as the face. Cure rates are equivalent to wide excision. Special training is required to perform this technique. An alternative method is
CCPDMA and can be performed by a pathologist not familiar with
Mohs surgery.
In the case of disease that has spread (metastasized), further surgical procedures or
chemotherapy may be required.
[50]
Reconstruction[edit]
Currently, surgical excision is the most common form of treatment for skin cancers. The goal of reconstructive surgery is restoration of normal appearance and function. The choice of technique in reconstruction is dictated by the size and location of the defect. Excision and reconstruction of facial skin cancers is generally more challenging due to presence of highly visible and functional anatomic structures in the face.
When skin defects are small in size, most can be repaired with simple repair where skin edges are approximated and closed with sutures. This will result in a linear scar. If the repair is made along a natural skin fold or wrinkle line, the scar will be hardly visible. Larger defects may require repair with a skin graft, local skin flap, pedicled skin flap, or a microvascular free flap. Skin grafts and local skin flaps are by far more common than the other listed choices.
Skin grafting is patching of a defect with skin that is removed from another site in the body. The skin graft is sutured to the edges of the defect, and a bolster dressing is placed atop the graft for seven to ten days, to immobilize the graft as it heals in place. There are two forms of skin grafting: split thickness and full thickness. In a split thickness skin graft, a shaver is used to shave a layer of skin from the abdomen or thigh. The donor site regenerates skin and heals over a period of two weeks. In a full thickness skin graft, a segment of skin is totally removed and the donor site needs to be sutured closed.
[52]
Split thickness grafts can be used to repair larger defects, but the grafts are inferior in their cosmetic appearance. Full thickness skin grafts are more acceptable cosmetically. However, full thickness grafts can only be used for small or moderate sized defects.
Local skin flaps are a method of closing defects with tissue that closely matches the defect in color and quality. Skin from the periphery of the defect site is mobilized and repositioned to fill the deficit. Various forms of local flaps can be designed to minimize disruption to surrounding tissues and maximize cosmetic outcome of the reconstruction. Pedicled skin flaps are a method of transferring skin with an intact blood supply from a nearby region of the body. An example of such reconstruction is a pedicled forehead flap for repair of a large nasal skin defect. Once the flap develops a source of blood supply form its new bed, the vascular pedicle can be detached.
[53]
Prognosis[edit]
The mortality rate of basal-cell and squamous-cell carcinoma is around 0.3%, causing 2000 deaths per year in the US. In comparison, the mortality rate of melanoma is 15–20% and it causes 6500 deaths per year.
[54]:29,31 Even though it is much less common, malignant melanoma is responsible for 75% of all skin cancer-related deaths.
[55]
The survival rate for people with melanoma depends upon when they start treatment. The cure rate is very high when melanoma is detected in early stages, when it can easily be removed surgically. The prognosis is less favorable if the melanoma has spread to other parts of the
body.
[56] As of 2003 the overall five year cure rate with Mohs' micrographic surgery was around 95 percent for recurrent basal cell carcinoma.
[57]
Australia and
New Zealand exhibit one of the highest rates of skin cancer incidence in the world, almost four times the rates registered in the United States, the
UK and
Canada. Around 434,000 people receive treatment for non-melanoma skin cancers and 10,300 are treated for melanoma. Melanoma is the most common type of cancer in people between 15–44 years in both countries. The incidence of skin cancer has been increasing.
[58] The incidence of melanoma among
Auckland residents of European descent in 1995 was 77.7 cases per 100,000 people per year, and was predicted to increase in the 21st century because of "the effect of local stratospheric ozone depletion and the time lag from sun exposure to melanoma development."
[59]
Epidemiology[edit]
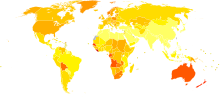
Age-standardized death from
melanoma and other skin cancers per 100,000 inhabitants in 2004
[60]
no data
<0.7
0.7–1.4
1.4–2.1
2.1–2.8
2.8–3.5
3.5–4.2
|
4.2–4.9
4.9–5.6
5.6–6.3
6.3–7
7–7.7
>7.7
|
Skin cancers result in 80,000 deaths a year as of 2010, 49,000 of which are due to melanoma and 31,000 of which are due to non-melanoma skin cancers.
[61] This is up from 51,000 in 1990.
[61]
More than 3.5 million cases of skin cancer are diagnosed annually in the United States, which makes it the most common form of cancer in that country. One in five Americans will develop skin cancer at some point of their lives. The most common form of skin cancer is basal-cell carcinoma, followed by squamous cell carcinoma. Unlike for other cancers, there exists no basal and squamous cell skin cancers
registry in the United States.
[62]
Melanoma[edit]
In the US in 2008, 59,695 people were diagnosed with melanoma, and 8,623 people died from it.
[63] In Australia more than 12,500 new cases of melanoma are reported each year, out of which more than 1,500 die from the disease. Australia has the highest per capita incidence of melanoma in the world.
[64]
Although the rates of many cancers in the United States is falling, the incidence of melanoma keeps growing, with approximately 68,729 melanomas diagnosed in 2004 according to reports of the
National Cancer Institute.
[65]
Melanoma is the fifth most common cancer in the UK (around 13,300 people were diagnosed with melanoma in 2011), and the disease accounts for 1% all cancer deaths (around 2,100 people died in 2012).
[66]
Non-melanoma[edit]
Approximately 2,000 people die from basal or squamous cell skin cancers (non-melanoma skin cancers) in the United States each year. The rate has dropped in recent years. Most of the deaths happen to people who are elderly and might not have seen a doctor until the cancer had spread; and people with immune system disorders.
[62]